In the opening days of October 2026, American biotechnology delivered a quiet but unmistakable milestone: the first administration of prime editing directly inside a living human body. Prime Medicine of Cambridge, Massachusetts, dosed the inaugural patient in its Phase 1/2 trial of PM577a, an investigational therapy for Wilson’s disease—an inherited disorder in which mutations in the ATP7B gene prevent the liver from clearing excess copper, with consequent damage to liver and nerves. Delivered by intravenous lipid nanoparticle and aimed at the common H1069Q variant, the treatment rewrites the defective sequence in hepatocytes in situ, without the prior extraction and laboratory reinfusion of cells that has characterized earlier gene therapies. Nature reported the dosing as the first known instance of this high-precision technique altering DNA inside a person; initial safety and efficacy data are not expected until 2027.
Prime editing differs from the original CRISPR-Cas9 approach in a decisive respect. Where the earlier system typically cuts both strands of DNA and relies on the cell’s error-prone repair machinery, prime editing nicks only one strand and supplies a reverse-transcriptase-guided template that rewrites the intended letters with greater fidelity. It is therefore suited to the precise correction of point mutations and small insertions or deletions that drive many monogenic diseases. Earlier clinical work by the same company had already applied the method ex vivo to blood stem cells in patients with a rare immune disorder; the Wilson’s trial marks the transition to true in vivo delivery, a step that, if successful, could reduce manufacturing complexity and broaden access for those rare conditions whose pathology is concentrated in an accessible organ such as the liver.
The advance remains early and narrowly scoped. No clinical outcome data yet confirm that the intended edit has been made, has persisted, or has improved copper handling. Even if those hurdles are cleared, the technology’s present reach is monogenic disease, not the redesign of complex human traits. Sexual orientation is polygenic and heavily influenced by non-genetic factors; no single “letter” or small cluster of letters has been shown to determine it, still less to admit of a therapeutic rewrite. Ancestral morphological variation is likewise the product of thousands of loci of small effect distributed across populations that have always been continuous rather than discrete. The temptation to treat either as a correctable defect confuses the repair of a broken copper transporter with the engineering of populations—an ambition for which current science supplies neither the mechanistic map nor the clinical warrant. The proper measure of this work is whether it can restore normal function to livers that cannot clear copper, not whether it can underwrite larger projects of human redesign.
Sec. HHS RFK Pulls Funding For mRNA Gene Therapy “Vaccine” Development
Population Genetics Validates Early Racial Observations Modern Anthropology Long Denied
15 Million People Fear For Their Genecic Data
Brain Cells Play Doom on Chip: Kaczynski’s Dystopian Vision Fulfilled

Scientists Deploy Prime Editing Inside the Human Body for First Time

Scientists Deploy Prime Editing Inside The Human Body For First Time by Grok is licensed under Grok xAI
Scientists Deploy Prime Editing Inside the Human Body for First Time

Byron Donalds Calls Man Sir Twice And Meltdown Erupts Instantly
Chimping Out And Mental Illness = Funny Combination!

Groypers Wave America First Flag as Melting Pot Forges Them
Speaking Of Gay...
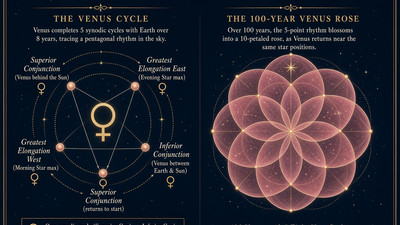
Venus Ends Century-Long Scorpio Cycle, Enters Libra’s Scales of Justice
Justice Is Coming???

Russian Diesel Tanker Heads to New York Under Trump Deal
Russians In NYC? Moscow Rules Apply! But This Friendly Exchange Is the Beginning Of The End. But Of What? Time Till Tell.

Trump, Vance Back Ramaswamy Ad as Ohio GOP Recoils
Repeal The 19th! Pajeet On The Street...Take America Back People!

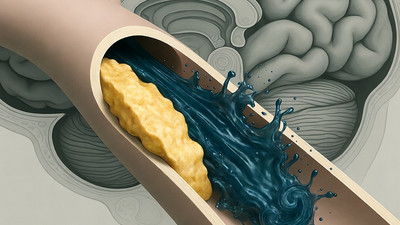
Scientists Clear Alzheimer’s Plaques From Brain in Minutes Without Drugs
Bones: "For God's Sake I Am A Doctor, Man!" - The Future Is Now!

DOJ Filing Names Omar as Ilhan Nur Said Elmi, Alias Omar
Gotcha Bitch!